
Treatment Planning Case Study
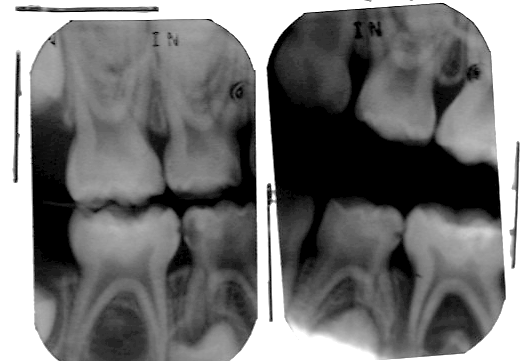
It’s always easier to understand something with an actual example. So we’ve added that here. We’ve tried to bring together some of the teaching covered so far into a real-life case.
Look at the bitewings and consider the attached bio of this patient.
The patient MF is a 5-year-old boy who has been referred to you for management of dental pain.
History of the presenting complaint
Pain on and off for several months from the lower right quadrant. MF was anxious, and his mother was very keen to have the tooth extracted.
Medical History
Nil relevant
Social History
Came with Mother and Father. two elder siblings, both had a history of dental treatment
Diet History
Drinks squash, fizzy drinks, enjoys sweet snacks
Toothbrushing
Once daily with child fluoride paste, unsupervised. They live in an area without water fluoridation.
Now, we need to think about formulating a plan. We will walk through this step by step, outlining what factors we consider.
What other factors from the history might be important
To plan the patient properly, the first thing we’ll need to understand is the severity of the pain. A 5-year-old might struggle to explain this clearly, so we’ll need to rely on other indicators. Does it affect sleeping or eating? Is analgesia required, and if so, how often?
Then we need to make some sort of assessment of anxiety. The family has said the child is anxious, but the family assessment can sometimes be misleading. In an ideal world, we might think about using an anxiety scale, but MF is probably a year or two young for that. So, we need to rely on other clues such as any previous experience at the dentist. Have they had treatment? If so – what was it? In this case, the fact the patient tolerated vertical bitewing radiographs is a good sign of co-operation.
What is the likely diagnosis?
Caries is the obvious one affecting most of the primary molars. The pulps look unaffected, with no furcation pathology. Teeth affected are: URDm, LLEo, LLDd, LRDd, LREm (FDI: 54m, 75o, 74d, 84d, 85m)
What is the plan
The starting point of most plans is prevention. And the starting point of any caries prevention plan is always fluoride. In this case, the patient needs to clean their teeth twice a day with an adult strength fluoride toothpaste. Then on top of that, you can consider two-four times yearly fluoride varnish. Oral hygiene instruction is important (such as supervised brushing and spitting, not rinsing), but fluoride is the key. Clearly, diet also needs consideration. Diet sheets and diet analysis have a role. But the evidence tells us that fluoride is the key.
Once you have the prevention sorted, then you can think about restorative treatment.
Restorative treatment
Several factors to consider here. What is the treatment aim, how severe is the pain (ie is there pulpal involvement), what is the patient level of anxiety?
Assuming no pulpal involvement, then the aim here is to make the biofilm accessible. Conventionally that would be by removing caries and placing a filling. Now we would look at sealing caries in. Looking at the x-ray, the LRD definitely needs a restoration, with a Hall crown being a simple option requiring low levels of cooperation. The URD & LLD might also benefit from Hall crowns, as the caries is likely to be into dentine. Remember that radiographs will always underestimate caries extent. The remaining teeth could be monitored, though the restoration in LLE might need careful inspection.
The above plan is achievable even for anxious patients. However, if the behaviour was an issue, you might consider using inhalation sedation. If the child was still anxious, then there is always General Anaesthesia (GA) — but in this scenario, that is an approach we would try and avoid. Why? The severity of the problem isn’t significant enough to justify a GA. Where behaviour was so challenging that even simple restorative techniques like Hall crowns were not possible, you might consider pushing the prevention (perhaps by adding on silver diamine fluoride) and then retrying treatment again after several months had passed.
What about if the LRD had irreversible pulpitis?
This makes things more complicated. In this circumstance, the tooth either needs a pulp treatment or to be extracted. In terms of function and risk of space loss, the Ds are not significant teeth. So our choice would probably be extraction. Given the history, you might decide to go straight to inhalation sedation. A general anaesthetic could also be considered (but would not be ideal and would need to include a plan for the other carious teeth).
Paediatric Dentistry for Non-Specialists







