Home / Healthcare & Medicine / Diagnostics / Fungal Diagnostics in Critically Ill Patients / Haematology oncology patient – continued

Haematology oncology patient – continued
Adilia Warris continues the case of an 8 year old boy diagnosed with high risk acute lymphatic leukaemia and developed fever (38.7°C).
In step 3.3, we introduced the case of an 8-year-old boy who was previously diagnosed with high risk acute lymphatic leukaemia and had developed a fever while being neutropenic during the induction phase of his treatment. Read below for the next part of the case and share your thoughts in the comments section.
The HRCT-thorax showed characteristic signs of a possible fungal infection, e.g. the dense nodule in the left lung on HRCT demonstrates the radiological ‘halo sign’, consistent with invasive pulmonary aspergillosis.
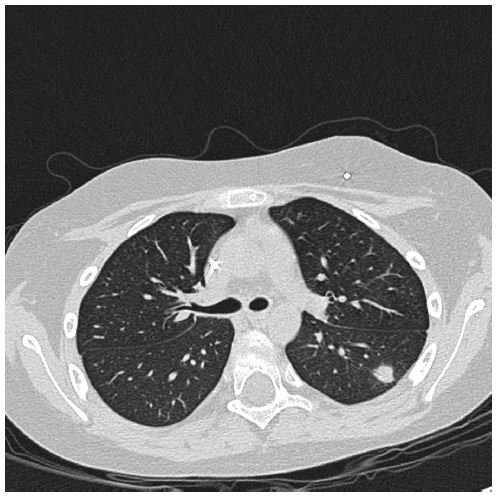
Due to the high likelihood of an invasive fungal infection, presumed to be caused by Aspergillus species due to positive GM in serum, a BAL was performed.
Direct microscopy of the BAL-fluid showed septated hyphae compatible with Aspergillus species but the culture remained negative. GM index in BAL fluid was 1.6.
Answer the following questions in the comment section below:
- What does the GM test result in the BAL fluid tell you?
- What is your diagnosis using the EORTC-MSG definition guidelines?
- Which antifungal(s) would you prescribe?
- Is there an indication to perform any additional diagnostic test(s)?
© BSAC
This article is from the online course:
Fungal Diagnostics in Critically Ill Patients
Created by

This article is from the free online
Fungal Diagnostics in Critically Ill Patients





