
Radiation therapy around the world
In 2012, 14.1 million new cases of cancer were reported worldwide and it is expected that this number will reach 24-6 million by 2030 (Jaffray et al, 2015). In the past, cancer was considered a problem mainly in high-income countries, but research has shown that more than half the cases of cancer in the world are found in people living in low and middle-income countries.
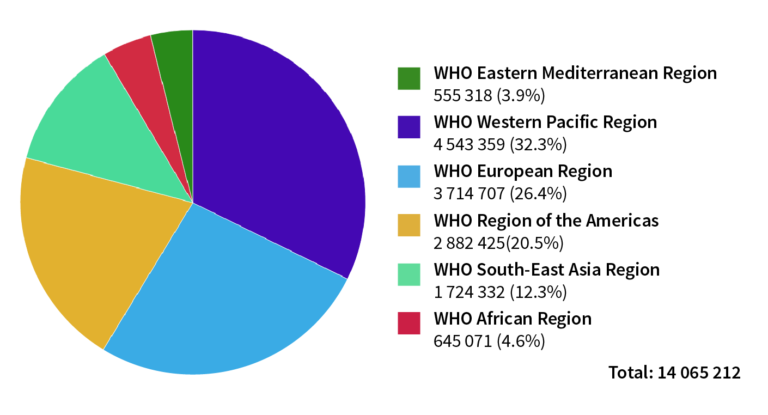 Estimated number of incident cases, both sexes, all cancers excluding non-melanoma skin cancer, worldwide in 2012. Data source: GLOBOCAN 2012. Graph production: Global Cancer Observatory ©International Agency for Research on Cancer 2018
Radiation therapy is an essential component of cancer treatment and care. It plays a role in both the curative (to help cure disease) and palliative (to relieve symptoms) management of cancer.
Approximately 50% – 60% of all cancer patients would benefit from radiation therapy as part of their primary treatment with up to 25% of patients benefiting from radiation therapy later in the cancer journey (Barton et al, 2006; Delaney, 2005). In many instances, lack of access to radiation therapy or significant delays result in unnecessary deaths.
Despite the proven benefits of radiation therapy, its use around the world is low. Access to radiation therapy has been reported to be inadequate even in very high-income countries. In many low and middle-income countries is it non-existent.
Let’s take a look at the figures from around the world
- In high income countries there are, on average, 1.9 treatment units per million population (or 13,951 machines).
- In low income countries the figure is 0.041 per million population or 26 machines (International Atomic Energy Agency Directory of Radiotherapy Centres, 2018).
- Twenty-two African and Asian countries have no radiation therapy service at all, with research in 2006 finding only 18% of the estimated need for radiation therapy in Africa.
- In many African countries there are only 2-3 radiotherapy machines for 40-50 million people leading to severe delays in treatment and pressure on utilisation.
- Shortages are also noted in Eastern Europe and Latin America (Barton et al, 2006).
 ©GlobalRT.org. GlobalRT is an initiative of UICC & GTFRCC.
Many factors have contributed to this inequality such as:
- How healthcare is financed in countries
- Lack of knowledge and promotion of the effectiveness of radiation therapy, both from a cost and outcome perspective
- Fear of radiation
- Fear of side effects previously associated with radiation therapy
The impact of unequal access to radiation therapy
Cancer is a wide range of distinct diseases requiring different treatment approaches but access to treatment should be guaranteed for all patients.
Scaling up radiation therapy from 2015-2035 could lead to a saving of 26.9 million life years in low and middle-income countries over the lifetime of the patients who receive treatment (Rifat et al, 2015). It is cost-effective and brings positive economic benefits in improving cure rates and quality of life for cancer patients.
Addressing inequality
The Global Task Force on Radiotherapy for Cancer Control (GTFRCC) was established in 2014 to calculate the magnitude of the gap between the current and the desirable access to radiation therapy.
Their focus was to bring attention to the severe shortages in radiation therapy and address how investment could be improved. In addition to calculating the costs, the Lancet Oncology Radiotherapy Commission also calculated the projected benefit from scaling up radiation therapy in terms of lives saved and return on investment. However, the challenge is huge and progress will take time. There is an urgent need for innovation and to engage the younger generation in the global radiation therapy effort.
Innovative approaches such as construction of fully functional modular approach to building comprehensive radiation therapy departments ‘radiation therapy units in containers’ are being considered as a rapid means to provide greater access. This work is ongoing together with encouragement to governments to prepare radiation therapy development plans in the wider cancer control context. This would be consistent with plans already developed in Canada, Australia, Ireland, the United Kingdom, The Netherlands, Brazil and India.
In the comments section below:
- Using the International Agency for Research on Cancer visualisation, explore the different cancer types on your continent.
- How does this compare to other continents?
- Why do you think your continent has high or low numbers for some cancers?
| Mary Gospodarowicz Mary Gospodarowicz is the former Medical Director of the Princess Margaret Cancer Centre at the University Health Network in Toronto, Canada and Regional Vice-President of Cancer Care Ontario for Toronto South. She is past President of the Union for International Cancer Control (UICC). |
 |
| Mary Coffey Mary Coffey is Adjunct Associate Professor at the Discipline of Radiation Therapy, Trinity College, Dublin, Ireland. She is a member of the International Atomic Energy Agency IAEA QUATRO Clinical Audit Team (2005 – present) and was the first Radiation Therapist (RTT) to be elected to the Board of the European Society of Radiotherapy and Oncology (ESTRO) in 2011. |
 |
An Introduction to Radiation Oncology: From Diagnosis to Survivorship


An Introduction to Radiation Oncology: From Diagnosis to Survivorship





